Quick Overview
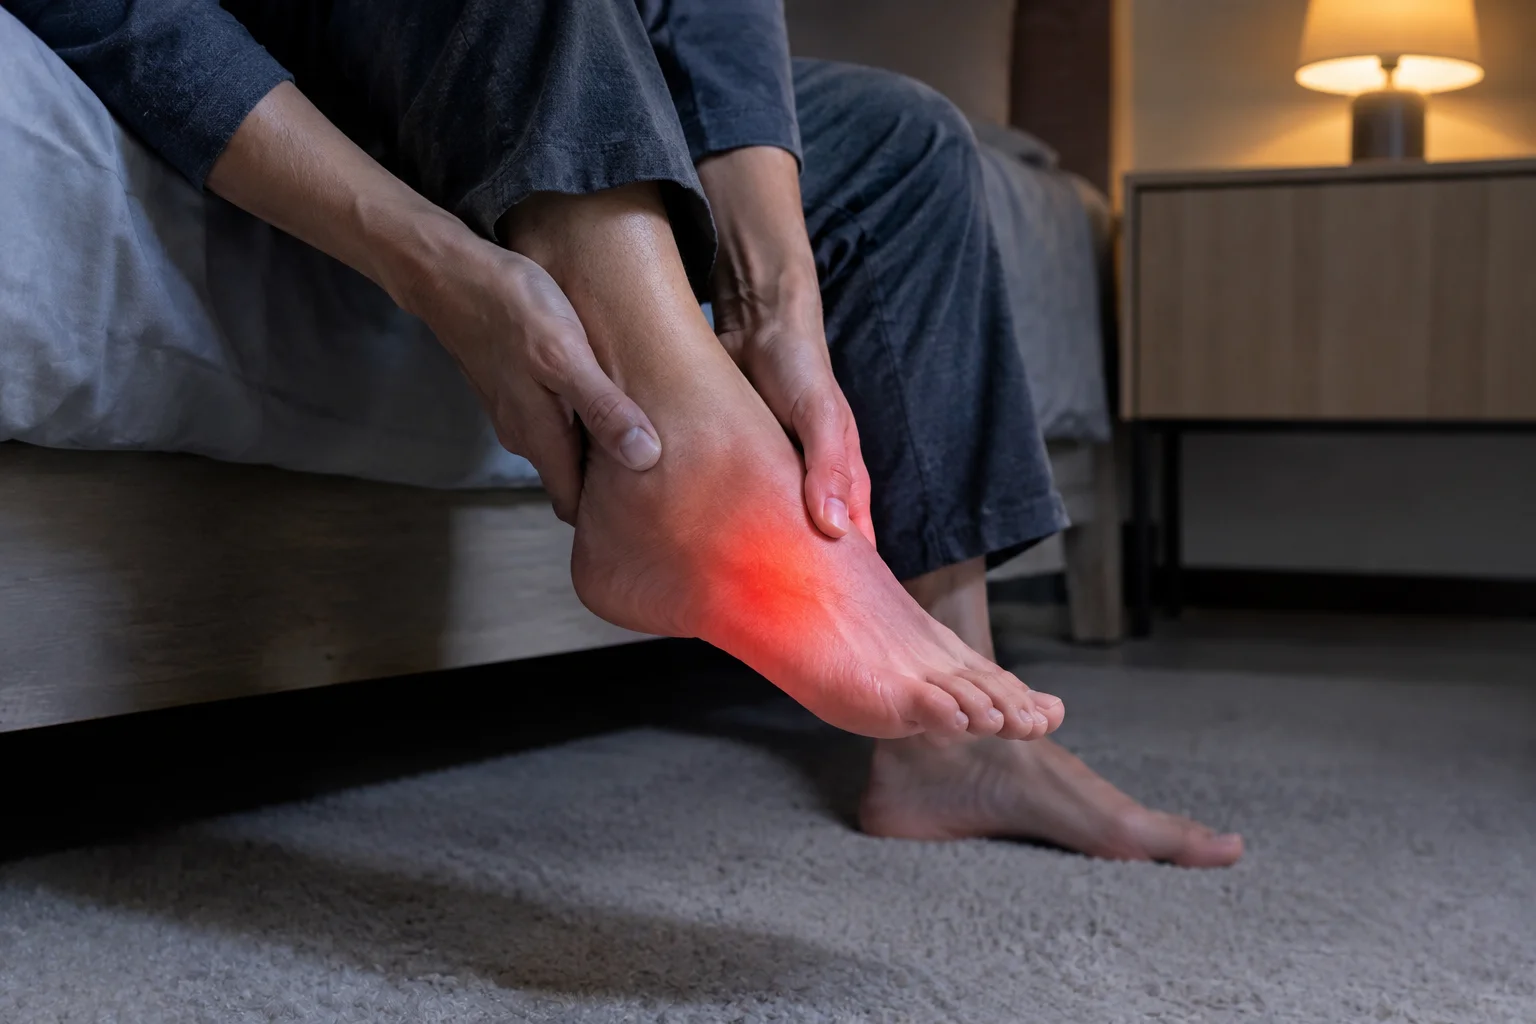
Stress fracture foot symptoms follow a distinct pattern that differentiates them from soft tissue injuries like plantar fasciitis, tendonitis, and muscle strains. The hallmark symptom is deep, localised pain at a specific point on the foot that worsens progressively with weight-bearing activity (walking, running, jumping), does not ease with warming up (unlike most tendon and muscle injuries), improves significantly with rest, and returns immediately when activity resumes. The pain is typically pinpointed to a specific bone rather than spread across a broad area. Swelling over the painful spot, tenderness when the bone is pressed directly, and pain that begins earlier in each successive activity session are all characteristic. The most commonly affected bones in the foot are the second and third metatarsals (the long bones in the midfoot), the calcaneus (heel bone), the navicular (midfoot), and the fifth metatarsal (outer foot).
At Sydney Foot Doctor, stress fracture diagnosis and management is a core component of our sports podiatry service across all eight Sydney clinics, and early diagnosis consistently leads to faster, simpler recovery.
What Is a Stress Fracture?
A stress fracture is a small, incomplete crack in a bone caused by repetitive loading that exceeds the bone’s ability to repair itself between sessions. Unlike a traumatic fracture (caused by a single impact, fall, or collision), a stress fracture develops gradually over days to weeks of cumulative overload.
Bones are living tissue that constantly remodels in response to the forces placed on them. When loading is applied gradually and followed by adequate rest, bones adapt and become stronger. When loading is applied too frequently, too intensely, or without sufficient recovery, the micro-damage accumulates faster than the bone can repair it. The result is a crack that worsens with every additional load cycle.
This is why stress fractures are overwhelmingly associated with repetitive activities: running, marching, dancing, basketball, and any sport or occupation involving sustained, repetitive foot impact. For a broader guide to running-related foot pain, read why does my foot hurt when I run.
The Key Symptoms: How to Recognise a Stress Fracture
Stress fracture symptoms follow a predictable progression that distinguishes them from other foot injuries.
| Symptom | What It Feels Like | Why It Points to a Stress Fracture |
|---|---|---|
| Deep, localised pain at a specific point | Aching or sharp pain felt at one precise spot on the foot, not spread across a broad area | Bone pain is localised to the fracture site. Soft tissue injuries tend to spread across a wider area. |
| Pain that worsens with activity | Pain increases during walking, running, or impact activity and does not ease with warming up | Tendon and muscle injuries often improve once warm. Stress fractures get worse with every step because each step loads the cracked bone. |
| Pain that improves with rest | Pain reduces significantly or disappears completely when you stop the activity and rest | The bone is no longer being loaded, so the pain source is eliminated. This is the classic rest-activity pattern of a stress fracture. |
| Pain that starts earlier each session | First noticed at the end of a run, then during the run, then at the start, then during walking | The crack is worsening with each loading session. Less force is needed to trigger pain because the bone is progressively weakening. |
| Swelling over the painful spot | Localised puffiness or swelling directly over the bone, not generalised foot swelling | The body’s inflammatory response concentrates at the fracture site. |
| Tenderness when the bone is pressed | Pressing directly on the bone produces sharp, localised pain | Direct pressure on the fracture site causes pain. Pressing adjacent areas does not. This “point tenderness” is highly characteristic. |
| Pain at night or at rest (advanced) | Aching or throbbing at the fracture site even without weight-bearing | Indicates the fracture has progressed significantly. The inflammatory response is now active even without loading. Seek assessment promptly. |
“The symptom that tells me it is a stress fracture rather than a tendon problem is the warming-up pattern. If a patient tells me the pain gets better once they warm up, I am thinking tendon. If they tell me the pain is there from the first step and gets worse the longer they go, I am thinking bone. That distinction changes everything about the management approach.”
Where Stress Fractures Occur: Location Matters
The location of the stress fracture in the foot determines the severity, the recovery timeline, and the treatment approach.
| Bone | Location in the Foot | How Common | Risk Level | Typical Recovery |
|---|---|---|---|---|
| Second metatarsal | Top of the foot, behind the second toe | Most common | Moderate | 6 to 8 weeks with rest and protected loading |
| Third metatarsal | Top of the foot, behind the third toe | Very common | Moderate | 6 to 8 weeks |
| Fifth metatarsal (base, Jones fracture zone) | Outer edge of the midfoot | Common in athletes | High | 8 to 12 weeks, may require immobilisation or surgery due to poor blood supply |
| Calcaneus (heel bone) | Deep within the heel, often mistaken for plantar fasciitis initially | Moderate | Moderate | 6 to 10 weeks |
| Navicular | Inner midfoot, behind the arch | Less common but serious | High | 6 to 12 weeks minimum, may require non-weight-bearing period |
| Sesamoids (under the big toe joint) | Underneath the ball of the foot at the big toe | Less common | Moderate to high | 8 to 12 weeks, often prolonged due to constant loading |
The second and third metatarsals are the most frequently fractured because they absorb the highest repetitive load during the push-off phase of walking and running. The fifth metatarsal base and the navicular are considered “high risk” stress fractures because the blood supply to these areas is limited, which slows healing and increases the risk of the fracture failing to unite (non-union) without appropriate management.
For calcaneal (heel) stress fractures that are initially mistaken for plantar fasciitis, the distinguishing feature is that plantar fasciitis pain is worst with the first morning steps and eases with movement, while a calcaneal stress fracture pain is constant during weight-bearing and does not improve with warming up.
What Causes Stress Fractures in the Foot
Stress fractures result from a mismatch between the load applied to the bone and the bone’s capacity to absorb and repair that load. Several factors contribute.
Training load errors are the primary cause. Increasing running distance by more than 10 percent per week, adding speed work or hill sessions without adequate base conditioning, returning to running too quickly after a break, and running on consecutive days without rest days all overload bone that has not had time to adapt.
Biomechanical factors determine which bone is overloaded. Overpronation increases stress on the navicular and second metatarsal. High arches concentrate load on the metatarsal heads and the calcaneus. Forefoot strike patterns without adequate conditioning increase metatarsal stress. A biomechanical assessment identifies your specific loading pattern, and custom orthotics redistribute the load across the foot to reduce concentrated stress on vulnerable bones.
Footwear that has lost its cushioning capacity (most running shoes degrade after 600 to 800 kilometres) transmits more impact force to the bones. Shoes that are too flexible, too flat, or wrong for the wearer’s foot type compound the problem. A footwear assessment ensures your shoes match your foot and your activity.
Nutritional factors affect bone density and healing capacity. Low calcium intake, low vitamin D levels (common in people who train indoors or use high-SPF sunscreen), and relative energy deficiency (not eating enough to support training load) all weaken the bone’s ability to withstand repetitive stress and repair micro-damage between sessions.
Bone density decreases with age and is affected by hormonal factors (post-menopausal women are at higher risk), medical conditions, and medications. People with lower bone density fracture under lower loads and heal more slowly.
Surface and terrain. Running on hard surfaces (concrete, asphalt) transmits more impact to the feet than softer surfaces (grass, trails, synthetic tracks). Abrupt changes from a soft training surface to a hard one increase stress fracture risk.
Stress Fracture vs Other Foot Injuries: How to Tell the Difference
Several foot conditions share symptoms with stress fractures. Knowing the differences helps you seek the right assessment.
| Condition | Key Differences from a Stress Fracture |
|---|---|
| Plantar fasciitis | Worst with first morning steps, eases with movement. Pain is under the heel at the fascia insertion, not deep within the bone. Responds to stretching. |
| Achilles tendonitis | Pain at the back of the heel or lower calf, not on the foot bones. Typically eases with warming up. Tendon is visibly thickened and tender to squeeze. |
| Metatarsalgia | Burning or aching under the ball of the foot, usually spread across multiple metatarsal heads. Related to pressure distribution, not a crack in the bone. Responds to orthotics and footwear changes. |
| Morton’s neuroma | Sharp, shooting pain between the third and fourth toes, often described as “walking on a marble.” Nerve-related, not bone. |
| Bunion pain | Pain at the big toe joint, associated with visible bump and angular deviation. Joint and soft tissue issue, not a bone crack. |
| Tendon strain | Broader, aching pain along the tendon’s path. Improves with warming up. No specific point tenderness on the bone. |
If you are unsure, the safest approach is to stop the aggravating activity and book a podiatric assessment. Continuing to load a potential stress fracture while waiting to see if it “gets better on its own” risks progressing a treatable crack into a complete fracture that requires immobilisation or surgery.
How Stress Fractures Are Diagnosed
Clinical assessment by a sports podiatrist is the starting point.
Clinical examination. Your podiatrist assesses the pain location, reproduction of pain with specific loading tests (hop test, single-leg loading, tuning fork test), swelling, point tenderness, and your training history. The clinical findings guide whether imaging is needed and which type.
X-ray is the first imaging step but has a significant limitation: stress fractures often do not appear on X-ray until two to four weeks after the fracture occurs, when the bone’s healing response (callus formation) becomes visible. A normal X-ray does not rule out a stress fracture if the clinical suspicion is high.
MRI is the gold standard for stress fracture diagnosis. It detects bone marrow oedema (swelling within the bone) at a much earlier stage than X-ray and identifies the fracture line itself. MRI also distinguishes stress fractures from other bone conditions (tumours, infections) that can mimic stress fracture symptoms. Your podiatrist refers for MRI when the clinical presentation is consistent with a stress fracture but X-ray is normal or inconclusive.
Bone scan is an alternative to MRI that detects increased bone activity at the fracture site. It is highly sensitive (picks up almost all stress fractures) but less specific than MRI (other conditions also cause increased bone activity).
Treatment and Recovery
Stress fracture treatment follows a structured protocol based on the fracture location and severity.
Immediate management: Offload the bone. Stop all activities that cause pain. This means no running, no jumping, and potentially reduced walking depending on the fracture location. Continuing to load a stress fracture delays healing, risks fracture progression, and can convert a simple stress fracture into a complete fracture requiring surgery.
Protected weight-bearing. Depending on the fracture location and severity, your podiatrist may recommend a moon boot (CAM walker) to protect the bone during healing, crutches to reduce weight through the affected foot, or stiff-soled shoes that limit bending at the fracture site. High-risk fractures (fifth metatarsal base, navicular) may require a period of complete non-weight-bearing.
Maintain fitness without impact. Swimming, cycling, and upper-body exercise maintain cardiovascular fitness and mental wellbeing during the recovery period without loading the fracture. Your podiatrist advises which activities are safe for your specific fracture.
Address the cause. During the recovery period, the factors that caused the stress fracture are addressed so it does not recur when activity resumes. Custom orthotics or sports insoles correct biomechanical overload. Footwear assessment ensures appropriate shoes. Nutritional factors (calcium, vitamin D) are addressed. Training load errors are identified and a graduated return-to-activity plan is created.
Graduated return to activity. Once clinical assessment confirms the fracture has healed (typically 6 to 12 weeks depending on the bone), activity is reintroduced gradually. The return protocol starts with walking, progresses to fast walking, then light jogging, then running at reduced volume and intensity, then full training over a period of two to four weeks. Jumping straight back to full training is the most common cause of re-fracture.
Adjunct therapies. Shockwave therapy may be used to stimulate bone healing in fractures that are slow to unite. Laser therapy can reduce pain and inflammation around the fracture site during the recovery period.
What Happens If You Ignore the Symptoms
Continuing to load a stress fracture is the most common and most costly mistake patients make.
The crack worsens. Each loading session extends the fracture line through more of the bone’s cross-section.
Pain escalates. What started as end-of-activity aching becomes constant pain during any weight-bearing, then pain at rest.
Complete fracture. A stress fracture that propagates through the entire bone becomes a complete fracture: the bone breaks fully, possibly displacing. This is a dramatically more serious injury requiring casting, immobilisation, or surgical fixation (screws, plates) and months of recovery.
Non-union. Some stress fractures (particularly navicular and fifth metatarsal base) can fail to heal if loading continues. The bone cannot bridge the gap because the micro-damage never gets a chance to repair. Non-union often requires surgery.
Compensatory injuries. Altering your gait to avoid loading the painful foot creates abnormal stress on other structures: the other foot, the ankles, the knees, and the hips. It is common to develop a secondary injury from the compensatory loading pattern.
Early diagnosis and six to eight weeks of managed recovery is always preferable to months of complicated healing, surgery, and rehabilitation from a fracture that was ignored.
When to See a Podiatrist
Book an assessment if you have localised pain at a specific point on your foot that worsens with activity and improves with rest. If the pain has been present for more than a few days and is not improving. If the pain started at the end of activity but is now present earlier or during walking. If there is visible swelling over the painful spot. If pressing directly on the bone produces sharp, localised pain. If you have recently increased your training load significantly. If you are a runner, dancer, or athlete in a repetitive-impact sport and the pain pattern matches the symptoms described above.
Sydney Foot Doctor diagnoses and manages stress fractures across eight Sydney clinics, all located inside medical centres. For children and adolescents experiencing activity-related foot pain, the children’s podiatry service provides age-appropriate assessment.
Stress Fracture Foot Symptoms: How to Recognise a Bone Injury
The key symptoms, where stress fractures occur, what causes them, and what happens if you keep going.
The Hallmark Symptoms
Localised Pain
Deep ache at one specific point on the bone. Not spread across a broad area. Pinpoint tenderness when pressed.
KEY DIFFERENTIATOR
Worsens with Activity
Pain increases during walking, running, impact. Does NOT ease with warming up (unlike tendon injuries).
Improves with Rest
Pain reduces or disappears when activity stops. Returns immediately when activity resumes.
Starts Earlier Each Time
First noticed at the end of a run. Then during. Then at the start. Then during walking. Getting worse.
Where Stress Fractures Occur
2nd and 3rd Metatarsals
Top of the foot behind the toes. Most common location. Absorb the highest repetitive load during push-off.
6 to 8 weeks recovery
5th Metatarsal Base (Jones)
Outer edge of the midfoot. High risk. Poor blood supply slows healing. May require immobilisation or surgery.
8 to 12 weeks, HIGH RISK
Navicular (Midfoot)
Inner midfoot behind the arch. High risk. Limited blood supply. May require non-weight-bearing period.
6 to 12 weeks, HIGH RISK
Calcaneus (Heel Bone)
Deep within the heel. Often mistaken for plantar fasciitis initially. Key difference: does not ease with warming up.
6 to 10 weeks recovery
Sesamoids (Under Big Toe)
Small bones under the big toe joint. Constant loading makes healing prolonged. Pain during push-off.
8 to 12 weeks recovery
Stress Reaction (Pre-Fracture)
Bone is overloaded but not yet cracked. Oedema visible on MRI. Faster recovery if caught at this stage.
BEST TIME TO CATCH IT
Stress Fracture vs Other Injuries
Stress Fracture (Bone)
Pain does NOT ease with warming up
Localised to one specific point on a bone
Gets worse with every session
Sharp point tenderness when bone is pressed
Tendon or Muscle Injury
Pain often eases with warming up
Spread across a broader area (along the tendon)
May improve with stretching and treatment
Tenderness along the soft tissue, not on bone
What Happens If You Keep Going
Crack Worsens
Each loading session extends the fracture line through more of the bone.
Pain Escalates
Activity pain becomes constant pain. Then rest pain. Swelling increases.
Complete Fracture
Bone breaks fully. May displace. Requires casting or surgical fixation. Months of recovery.
Non-Union or Surgery
Bone fails to heal. Surgery needed. Return to sport delayed by months beyond the original recovery time.
💡 The Key Takeaway
The defining feature of a stress fracture is pain that worsens with activity and does not improve with warming up. If your foot pain follows this pattern, stop the aggravating activity and book a podiatric assessment. Six to eight weeks of managed recovery is always better than months of complicated healing from a fracture that was ignored.
sydneyfootdoctor.com.au | Sydney Foot Doctor | 8 Clinics Across Sydney